A nose does not block in one place
This is the part that decides whether an operation will help you, and it is the part most often skipped.
There are three places a nose narrows, and they are not interchangeable.
The septum. The midline partition between the two sides. When it is deviated it narrows one side, sometimes both at different heights. Septoplasty straightens it.
The turbinates. Ridges on the side walls that warm and humidify air. They swell, and in some people they are simply bulky. Reducing them is a turbinoplasty, and it is often done at the same time as other work.
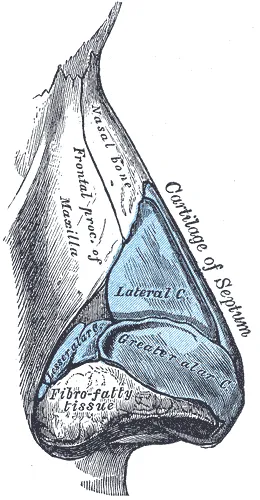
The nasal valve. The narrowest part of the whole airway, formed by the angle of roughly ten to fifteen degrees between the upper lateral cartilage and the septum, with the head of the inferior turbinate below it. Because it is the narrowest point it accounts for more than half of the resistance in the entire nose, and it is the part that draws inwards when you breathe in hard.
Septoplasty reaches the first of those three and not the third. If your obstruction is at the valve, straightening the septum alone will not fix it, because the valve is formed by the external structure of the nose and is reached from outside. That is what functional rhinoplasty is for, and it is why a nose can be operated on once for breathing and still not breathe.
What the three words actually mean
The terms get used loosely, including by surgeons.
- Septoplasty is the septum alone. Inside the nose, no change to the shape.
- Rhinoplasty is the external structure: the bones and cartilages that set the shape, and the valve.
- Septorhinoplasty is both in the one operation. The septum straightened and the external structure altered at the same sitting.
Functional rhinoplasty is not a fourth operation. It describes the reason for doing the second or the third: the work is directed at how the nose works rather than at how it looks. In practice the two are rarely separable. Septoplasty does not change the shape of the outside of the nose, but altering the outside shape changes the airway whether or not that was the aim, which is why I assess both together.
I assess both at every consultation rather than treating function as an add-on.
What the operation involves
Through the nostrils, or through a small incision across the strip of skin between them where the external structure needs more exposure. The septum is straightened, and cartilage taken from it is often the graft material used to support the valve or the tip. Where the valve is the problem it is usually widened with a graft placed to hold it open, rather than by removing anything.
Turbinate reduction is frequently done at the same time.
I use ultrasonic instruments for the bony work in all of my rhinoplasty cases. Preservation technique is a separate approach that I use where the anatomy suits it, and that is an anatomical decision rather than a preference.
Recovery
Most people are off work for 10 days to two weeks. The splint comes out at your review, between seven and ten days after surgery, and breathing is often worse before it is better, because the lining is swollen from the surgery itself. That settles over a few weeks.
The nose feels blocked for longer than patients expect. Airflow usually improves steadily across the first two to three months, and the external shape is not settled for about twelve months. No technique shortens that.
Medicare and health funds
This is the question I am asked most often and it has a real answer, with a real limit.
Surgery done to correct a functional problem is done for a medical reason, and is commonly covered in part by Medicare and health funds. Surgery done to change the appearance of the nose is not. Where an operation does both and the criteria below are met, a rebate may still apply.
For rhinoplasty, Medicare requires either airway obstruction with a self-reported NOSE Scale score above 45, or a significant acquired, congenital or developmental deformity, such as a nose that changed shape after an injury or fracture, or one that is deviated or malformed from birth. Photographs or the NOSE Scale score must be documented in your notes. Where those criteria are met, a Medicare rebate may apply to the operation, whether or not it also changes how the nose looks.
The limit is this: what qualifies is decided by the findings, not by the reason you came in. I cannot describe a cosmetic operation as functional, and I would not. If there is an obstruction, it is documented and the appropriate item numbers are used. If there is not, the operation is a cosmetic one and is quoted that way.
You will be given the item numbers before surgery so you can check them with your fund and with Medicare yourself. There is more detail on the cost page, including the separate accounts from the anaesthetist and the hospital.
What it will not fix
Breathing can be improved and it can also be made worse, particularly where the valve is already narrow and the nose is being reduced. That is a real risk of the operation and it is the reason the assessment matters more than the technique.
Beyond that, some causes of a blocked nose are not structural and surgery does not reach them:
- Allergic rhinitis. The lining swells. Medical treatment comes first, and allergies change surgical outcomes when they are not controlled.
- Chronic sinus disease. A different problem with different surgery, sometimes done at the same time.
- A nose that feels blocked and measures open. It happens, and operating on it does not help.
Where this sits in what I do
A large part of my practice is functional. I see patients referred for breathing who have never considered the shape of their nose, and patients who came about the shape and leave having had the airway explained to them for the first time.
I do not offer surgery to everyone who consults me. If your nose is blocked for a reason surgery will not change, I will tell you that instead of operating.
You will need a referral. It is required before any surgery that changes the appearance of the nose, and it also lets you claim the consultation through Medicare. If you have had surgery before and still cannot breathe, bring the operation notes if you can get them.
Before and after
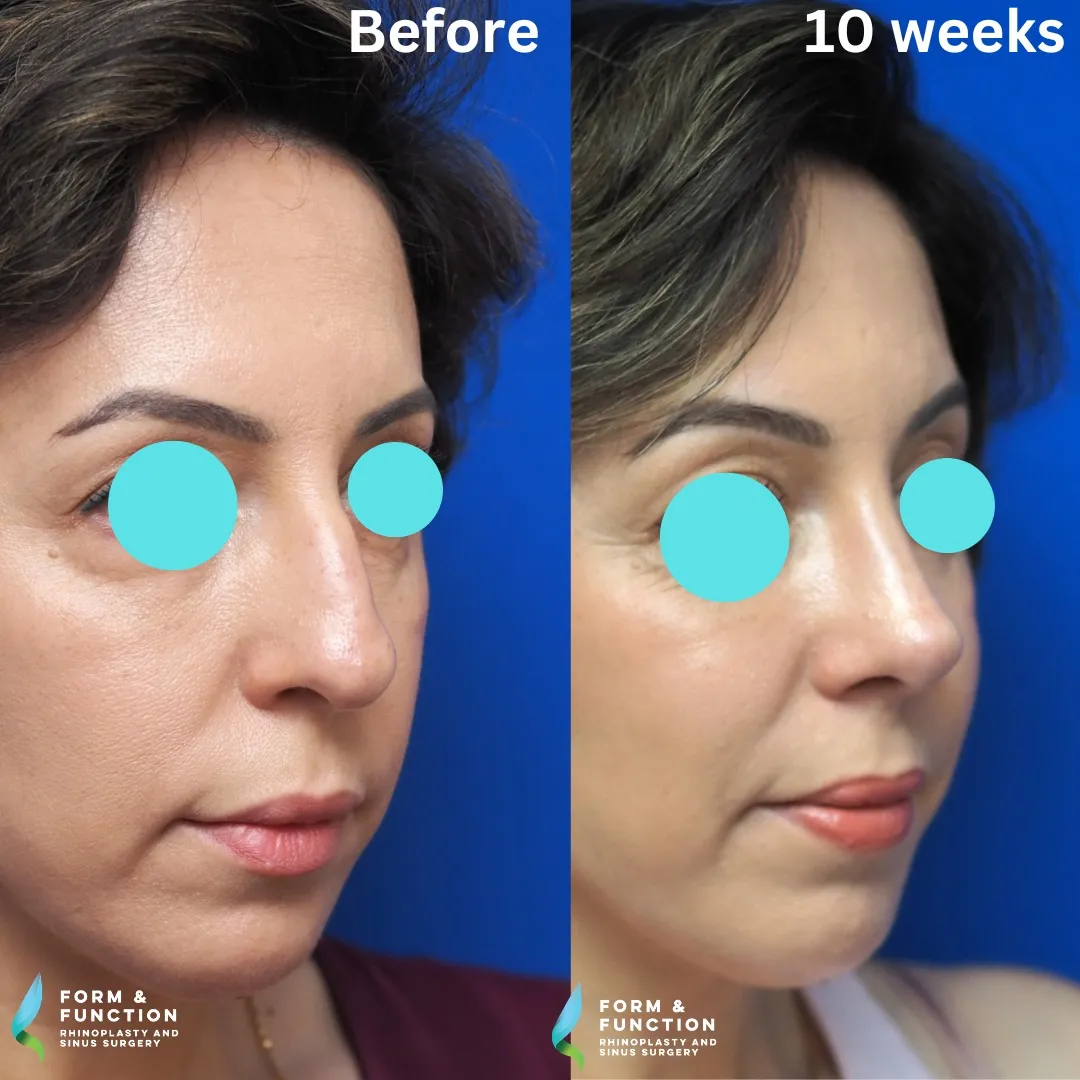
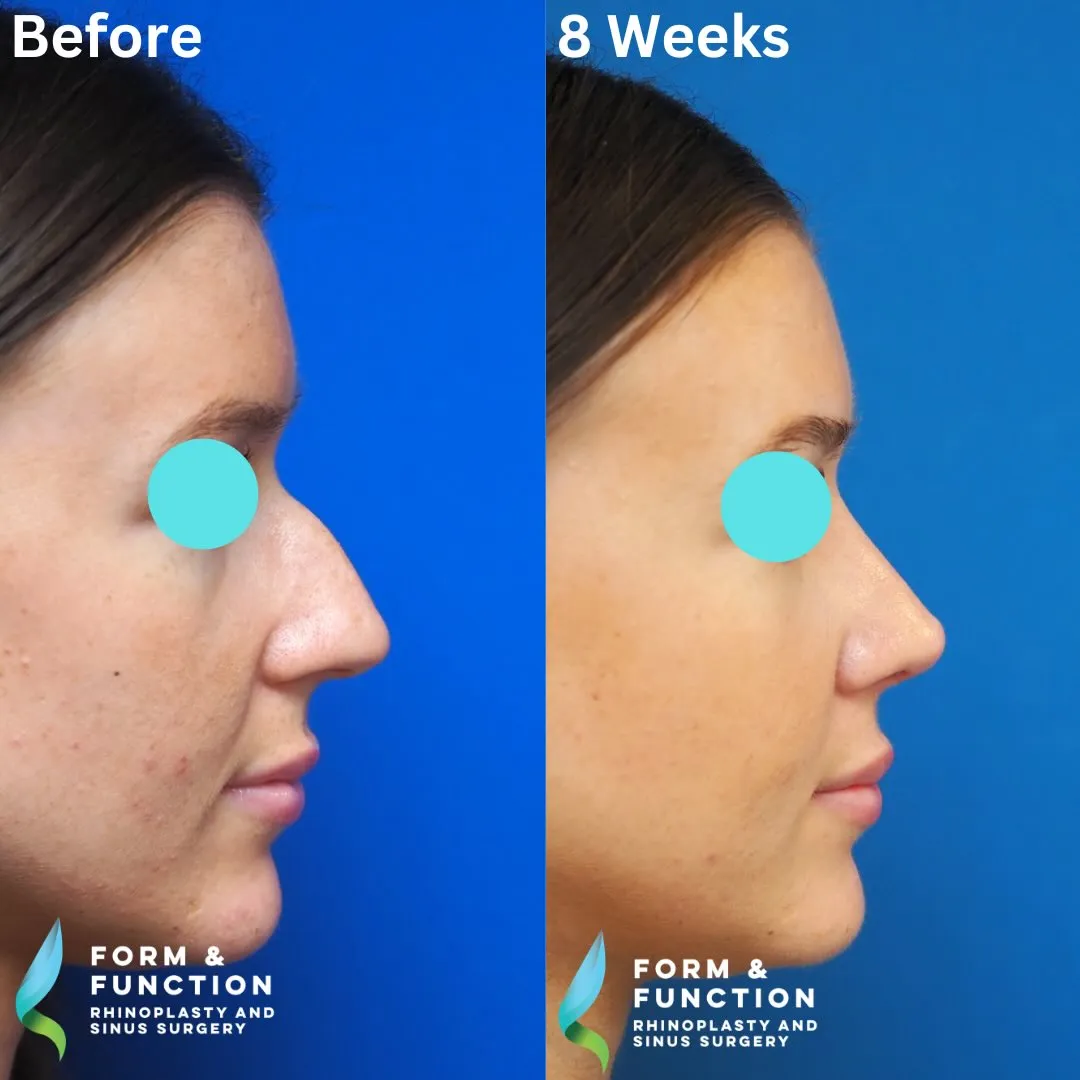
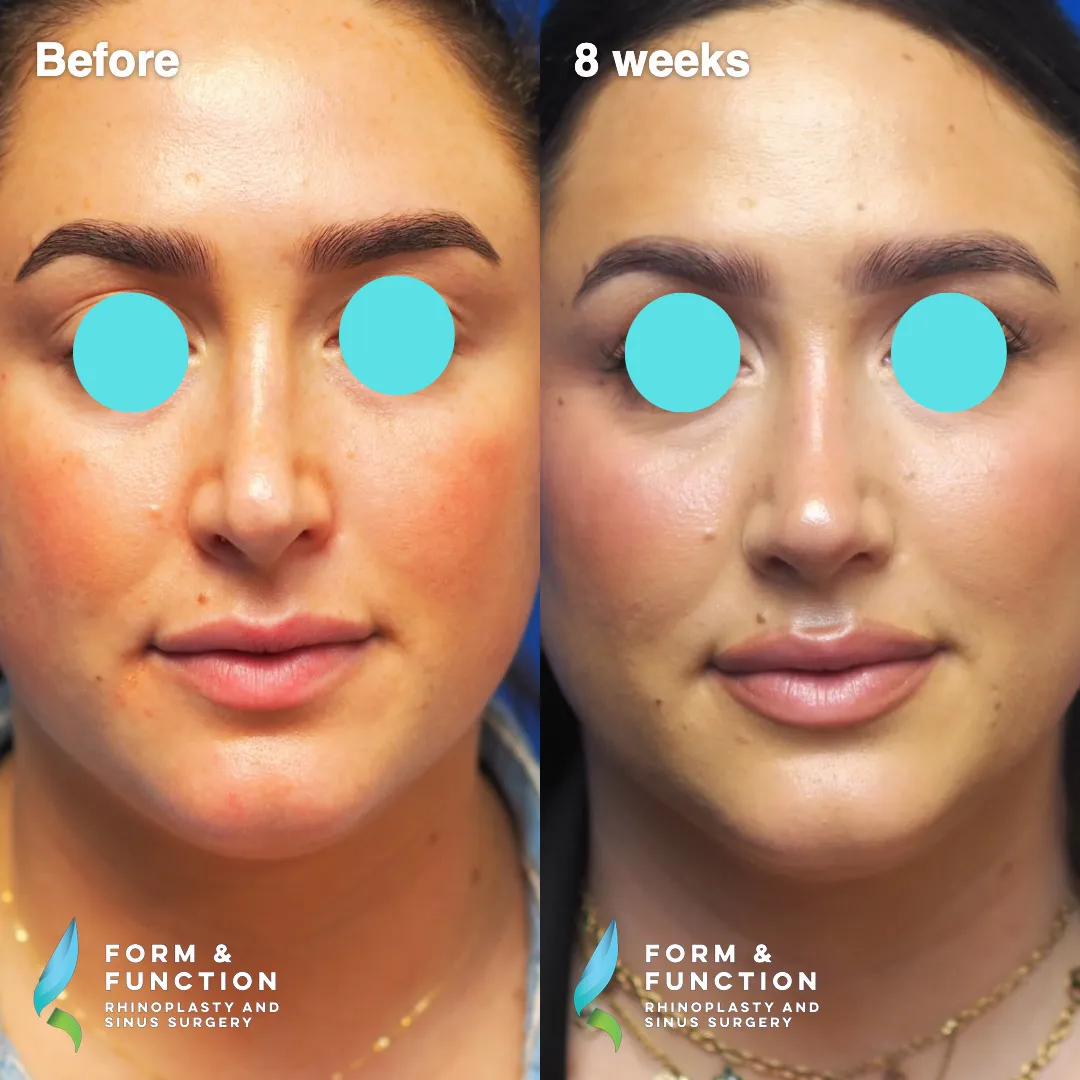
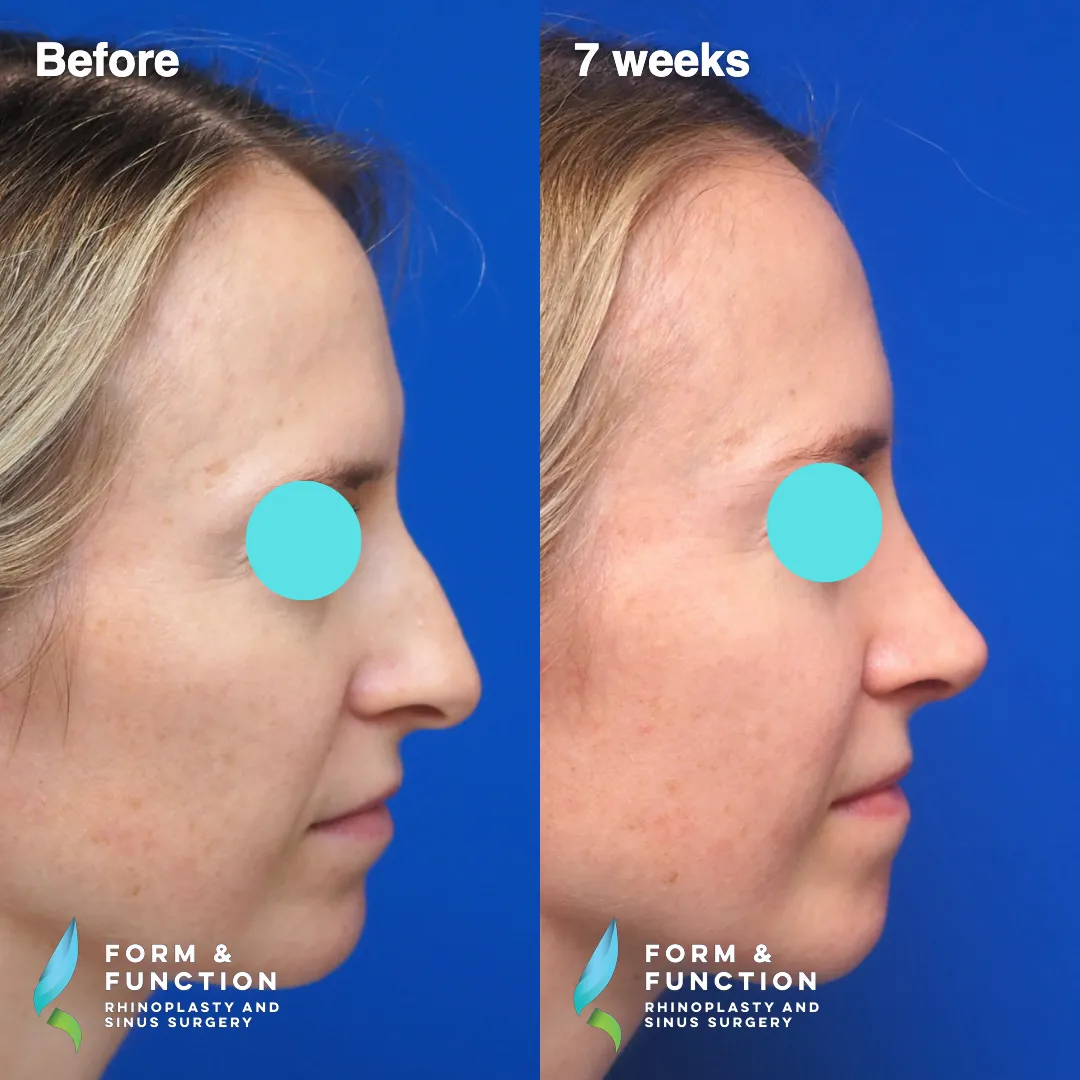
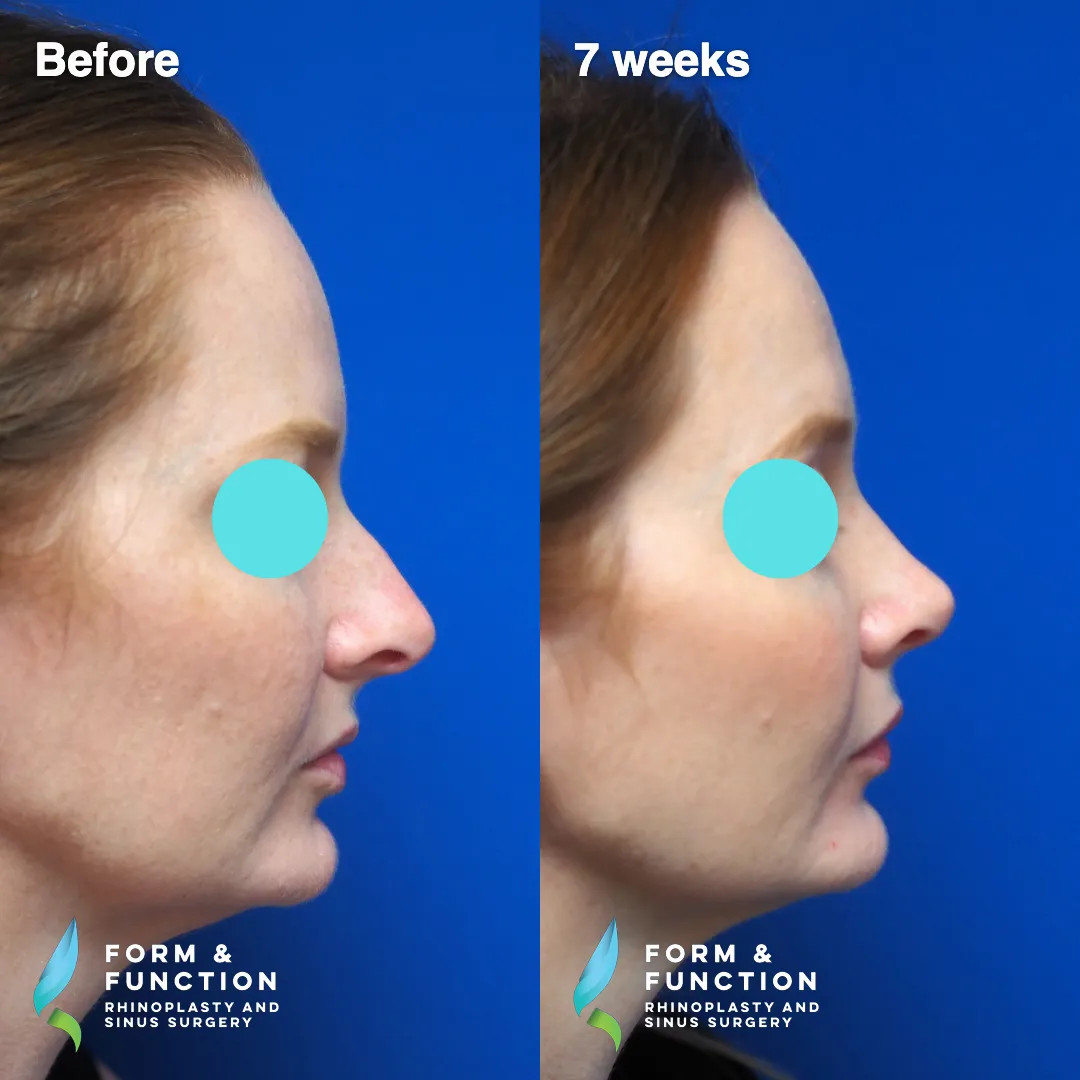
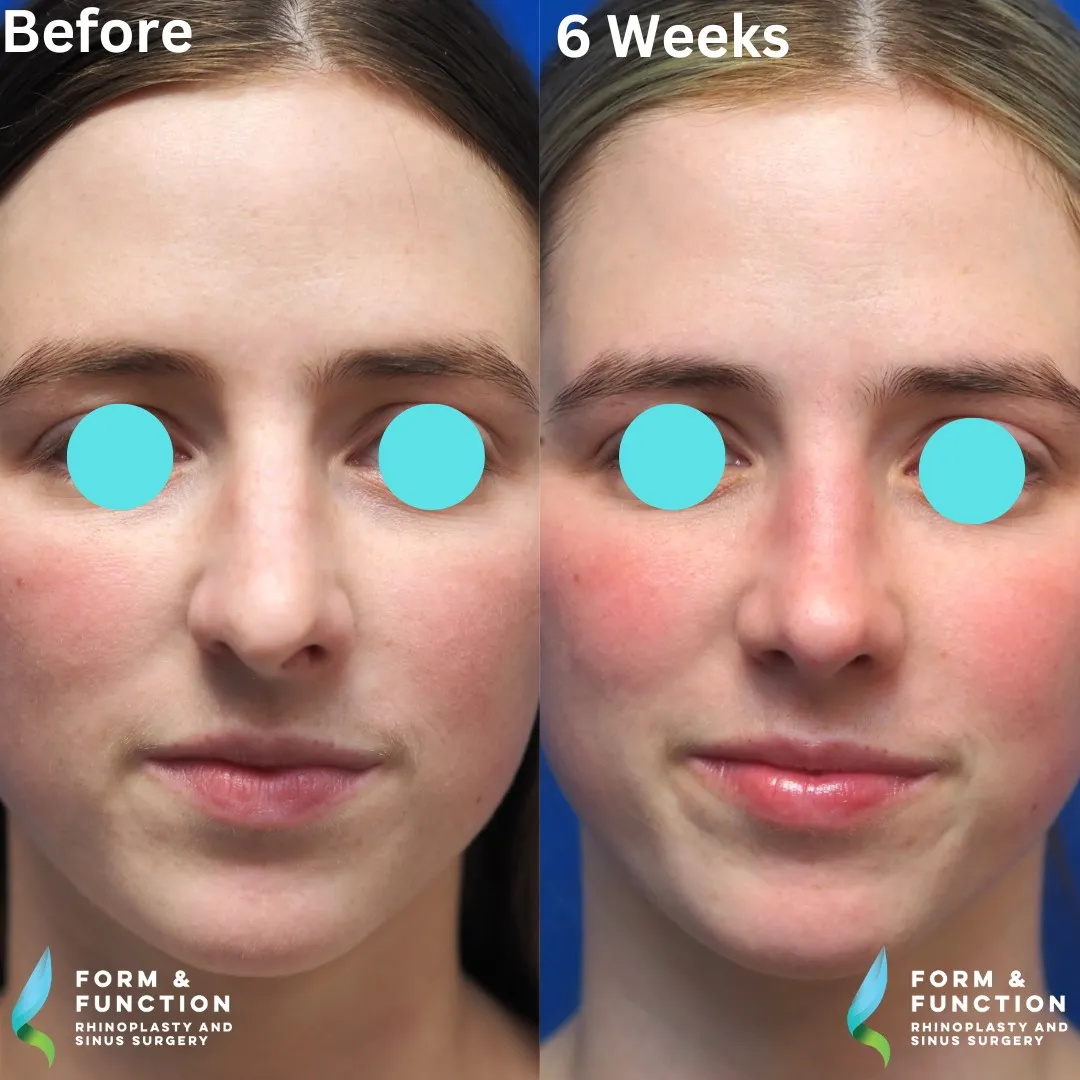
Patients who had the septum straightened as part of their operation, with the time since surgery stated on each photograph.